Prepared by the LSE Editorial Team. Reviewed by Joseph Andrade, Jr., RN, NRP.
Joseph is an active firefighter, paramedic, and registered nurse working in emergency and vascular access care, as well as an OSHA Outreach instructor and safety officer. He has spent his career on the response side of emergencies, from the fireground to the ambulance to the hospital bedside, and now trains civilians, workplaces, and first responders in the skills that save lives.
A national analysis of more than 45,000 pediatric out-of-hospital cardiac arrests found that where a child was treated may have influenced whether resuscitation was withheld or stopped. The study raises difficult questions about protocols, systems, transport, medical control, and consistency.
✅ Key Takeaways
- A 2026 Pediatrics study analyzed 45,045 nontraumatic pediatric out-of-hospital cardiac arrest encounters from 6,550 EMS agencies.
- EMS considered resuscitation futile in 6.6% of encounters. Among children for whom resuscitation was attempted, termination of resuscitation occurred in 25.4%.
- Agency-level variation was substantial. The modeled agency effect for termination of resuscitation exceeded the measured effect of every fixed patient factor in the study.
- The study does not prove that any particular agency made the wrong decision.
- The 2025 AHA/AAP resuscitation guidelines support on-scene resuscitation in most OHCA situations and recognize a role for field termination of resuscitation, while emphasizing system protocols and training.
- Pediatric TOR remains a high-stakes decision that should follow local protocols, medical direction, applicable law, and patient-specific circumstances.
▸ The question is uncomfortable because the patient is a child
Termination of resuscitation is one of the hardest decisions in emergency medicine. Adult EMS systems have decades of research and operational experience behind many TOR rules. Pediatric cardiac arrest is less common, the causes are different, and clinicians may have far fewer opportunities to make that decision.
A new national study in Pediatrics found substantial agency-level variation in decisions to withhold or terminate pediatric resuscitation. The finding does not tell us which agencies were right or wrong, but it gives EMS systems a reason to examine how those decisions are being made.
📊 What the researchers studied
Researchers examined nontraumatic out-of-hospital cardiac arrest encounters involving patients younger than 18 years using National EMS Information System data from 2018 through 2023.
The analysis included:
- 45,045 pediatric OHCA encounters,
- 6,550 EMS agencies,
- determinations that resuscitation was futile and therefore withheld,
- and termination of resuscitation after efforts had begun.
The authors used mixed-effects models to examine patient and agency factors and to quantify agency-level variation.
This is important because the study was not simply asking whether certain patient factors predicted resuscitation decisions.
It was asking whether the agency itself appeared to matter.
📊 What the study found
EMS considered resuscitation futile in 6.6% of the pediatric OHCA encounters.
Among children in whom resuscitation was attempted, prehospital termination of resuscitation occurred in 25.4%.
Several patient and event characteristics were associated with those decisions.
Futility determinations were less likely when:
- the arrest was witnessed,
- bystander CPR occurred,
- the event occurred in a public location,
- or the etiology involved respiratory/asphyxial causes or drowning.
The analysis also found substantial agency-level variation.
The median odds ratio for a futility determination was 2.33.
For termination of resuscitation, the median odds ratio was 3.50.
That agency-level TOR effect exceeded the measured effect of every fixed patient factor included in the model.
The authors concluded that local EMS practice patterns may shape pediatric resuscitation decisions.
The finding needs careful interpretation.
📊 What this study does not prove
The study does not tell us that agencies with higher TOR rates were wrong.
It does not tell us that agencies with lower TOR rates were better.
It does not establish the ideal pediatric TOR rate.
It does not tell us whether individual clinicians followed their local protocols correctly.
It also cannot capture every circumstance that affects a real resuscitation decision.
NEMSIS data are powerful for national system-level research, but retrospective registry studies are limited by documentation, variable definitions, missing clinical detail, and factors that may not be recorded.
The study’s practical message is that the variation is large enough for systems to investigate their own practice.
▸ Futility and TOR are not the same decision
The study separated two related but distinct outcomes.
Futility
In this analysis, futility referred to EMS withholding resuscitative efforts.
That may occur when death is clearly irreversible or when local protocols identify circumstances in which resuscitation should not be initiated.
Examples vary by law and protocol and may include obvious signs of irreversible death or valid medical orders.
Termination of resuscitation
TOR occurs after resuscitative efforts have begun and the team determines that continued efforts are unlikely to result in meaningful benefit.
That decision can involve:
- duration of resuscitation,
- rhythm,
- response to treatment,
- witnessed status,
- bystander CPR,
- etiology,
- physiologic data,
- reversible causes,
- transport considerations,
- protocol criteria,
- medical control,
- and local law.
For pediatric patients, the emotional and operational burden is substantial.
▸ The 2025 guidelines make this more relevant, not less
The 2025 American Heart Association and American Academy of Pediatrics resuscitation guidance places renewed emphasis on high-quality on-scene OHCA resuscitation.
The AHA Systems of Care guidance notes that on-scene resuscitation focused on achieving sustained ROSC before transport can be beneficial for most adults and children in the absence of special circumstances.
That approach has an unavoidable consequence:
If most resuscitation occurs on scene, EMS systems must be prepared to terminate resuscitation on scene when appropriate.
The 2025 guidance therefore also emphasizes death-notification training for EMS clinicians.
This is not an argument for ending pediatric resuscitation earlier.
It is an argument for systems to have a deliberate, evidence-informed process rather than relying on ad hoc decisions.
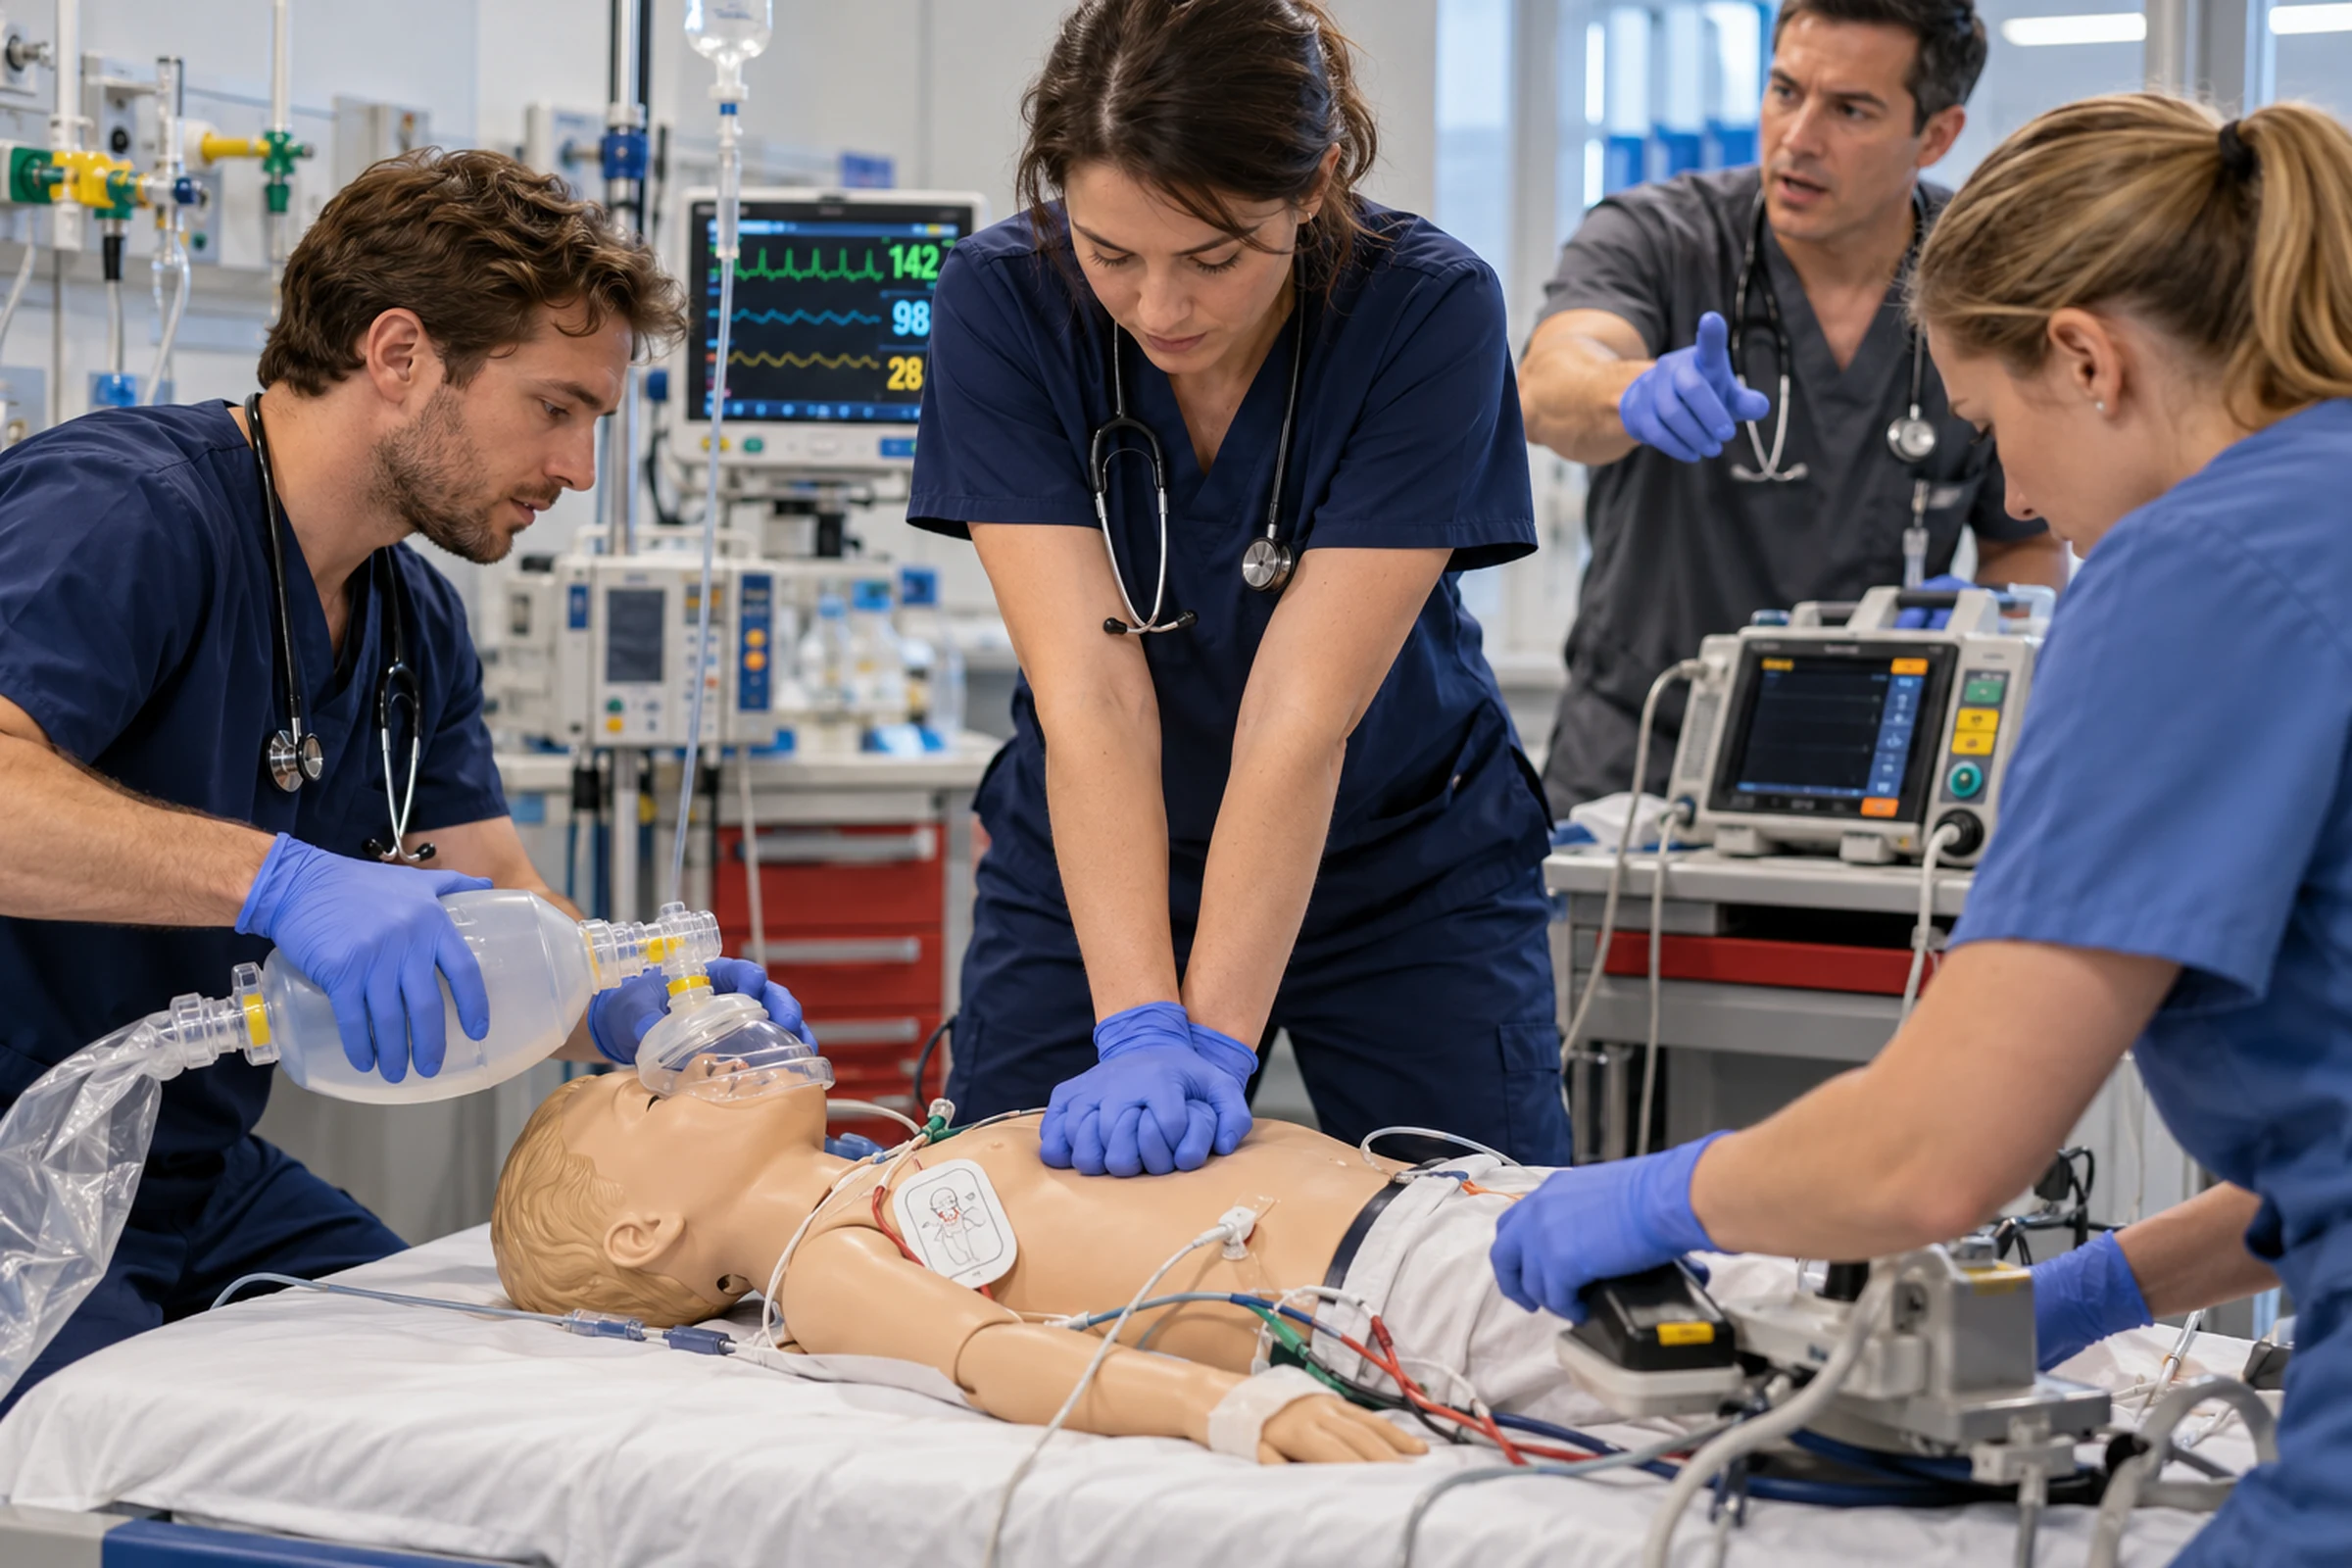
🚑 Pediatric arrest is not simply adult arrest in a smaller patient
Pediatric cardiac arrest often reflects different causes than adult arrest.
Respiratory failure, asphyxia, drowning, trauma, sudden unexpected collapse, congenital disease, and other etiologies may be involved.
Ventilation is especially important in many pediatric arrests.
The 2025 pediatric guidelines continue to emphasize high-quality CPR with ventilation and treatment of reversible causes.
That difference matters when thinking about termination.
A child with an asphyxial arrest, drowning event, hypothermia, or another potentially reversible cause may require a different decision process than an adult with an unwitnessed presumed primary cardiac arrest.
Blanket rules can be dangerous when the pathophysiology differs.
▸ Why agency culture may matter
The study did not directly measure culture, but agency-level variation can arise from many sources.
Potential contributors include:
- written protocols,
- medical-director philosophy,
- rural versus urban transport realities,
- access to online medical control,
- pediatric call volume,
- clinician experience,
- local legal requirements,
- hospital distance,
- training quality,
- availability of pediatric equipment,
- community expectations,
- and informal norms.
Two agencies can read the same evidence and operationalize it differently.
So system design matters.
▸ Transport is not automatically the safer choice
Pediatric cardiac arrest creates enormous pressure to transport.
A child is critically ill.
The family wants movement.
Clinicians may feel that remaining on scene looks like inaction.
But transporting during active CPR introduces real problems.
Moving CPR into a vehicle can compromise compression quality.
Rescuers may be unrestrained.
Airway and vascular access become more difficult.
The ambulance environment becomes crowded.
Lights-and-siren transport creates roadway risk for clinicians and the public.
A hospital does not automatically provide benefit if the interventions that matter most can already be delivered well on scene.
That is one reason the 2025 guidelines favor on-scene resuscitation in most OHCA situations unless special circumstances justify transport.
🚑 But pediatric exceptions matter
This is not a rule to never transport a child in arrest.
Potential reasons for transport may include circumstances such as:
- specific reversible etiologies,
- hypothermia,
- selected toxicologic emergencies,
- trauma systems,
- extracorporeal CPR pathways,
- local protocol,
- unusual operational factors,
- or situations where a hospital can provide an intervention unavailable in the field.
Transport decisions still need to account for the cause of arrest, available interventions, local protocol, and system capabilities.
▸ ETCO2 should not become a single-number TOR rule
The 2025 pediatric advanced life support guideline specifically cautions against using end-tidal carbon dioxide alone to make pediatric termination decisions.
Studies have documented survival even among pediatric patients with low ETCO2 values during resuscitation.
That is an important teaching point.
Physiologic monitoring can inform resuscitation quality and prognosis.
It should not become a simplistic single-number trigger to stop care.

▸ What should EMS medical directors ask?
The study offers a practical quality-improvement opportunity.
Every EMS system that treats children should be able to answer:
Do we have explicit pediatric TOR guidance?
If the protocol is vague, clinicians may make very different decisions.
Do clinicians know when medical control is required?
Ambiguity at the bedside can create delay, unnecessary transport, or inconsistent termination.
Do we review pediatric arrests?
Pediatric arrests are uncommon enough that each case can provide substantial learning.
Are decisions consistent across crews?
A system should understand whether outcomes change dramatically based on which shift, station, or clinician responds.
Do we train death notification?
If on-scene TOR is part of the system, clinicians need training in communicating with families.
Do we prepare clinicians for the emotional burden?
Ending resuscitation in a child can be psychologically difficult even when the decision is clinically appropriate.

▸ What should instructors change?
The study should not be turned into a new rule or algorithm.
It should be used to improve clinical reasoning.
A useful simulation can present a prolonged pediatric arrest and require learners to identify:
- reversible causes,
- quality of CPR,
- ventilation adequacy,
- rhythm,
- medication timing,
- transport considerations,
- local TOR criteria,
- medical-control requirements,
- and family communication.
Then ask the team:
What information would you need before you could justify stopping?
That question teaches more than memorizing a number.
▸ The fairness question
The most challenging finding is that agency-level variation was large.
That raises a system-level equity question:
Should a child’s chance of continued resuscitation depend heavily on which EMS agency happens to respond?
Some variation will always be appropriate because geography, resources, law, and patient factors differ.
But unexplained variation should not be ignored.
Systems should be able to explain why their practice looks the way it does.
If the answer is “That is just how we have always done it,” the system has work to do.
✅ What to remember
The new Pediatrics study does not provide a new pediatric termination-of-resuscitation rule.
It does something more foundational.
It shows that pediatric futility and TOR decisions vary substantially across EMS agencies even after researchers account for measured patient and event factors.
That should prompt medical directors, educators, and EMS leaders to examine their own systems.
Pediatric TOR should be:
- protocol-driven,
- medically defensible,
- consistent with current resuscitation guidance,
- sensitive to reversible causes,
- compliant with local law,
- supported by medical control when required,
- and taught as both a clinical and communication skill.
Agencies do not need identical TOR rates. They do need to know whether their differences can be explained by clinical factors, protocol, geography, resources, and other defensible system choices.
❓ Frequently Asked Questions
Did the study prove that some EMS agencies terminate pediatric resuscitation too often?
No. The study demonstrated substantial agency-level variation. It did not establish an ideal TOR rate or determine that a specific agency’s decisions were correct or incorrect.
How large was the study?
The analysis included 45,045 nontraumatic pediatric OHCA encounters involving 6,550 EMS agencies in NEMSIS data from 2018 through 2023.
Does the 2025 AHA guidance support on-scene pediatric resuscitation?
The 2025 Systems of Care guidance supports ongoing resuscitation at the scene for most OHCA cases, including pediatric patients, when special circumstances do not justify early transport. That makes high-quality TOR protocols and death-notification training important components of EMS systems.
Can ETCO2 be used alone to decide when to stop pediatric CPR?
No. The 2025 pediatric advanced life support guidance cautions against making pediatric TOR decisions based on ETCO2 alone. Low ETCO2 values do not make survival impossible.
Should adult TOR rules automatically be applied to children?
No. Pediatric arrest etiologies, physiology, system considerations, and evidence differ. EMS clinicians should follow their pediatric protocols, medical direction, applicable law, and current pediatric resuscitation guidance.
Why might agencies have different TOR practices?
Possible contributors include protocol wording, medical-direction philosophy, transport distance, clinician experience, pediatric call volume, local law, access to online medical control, community expectations, training, and system culture. The study demonstrates variation but does not prove which of these factors caused it.
▸ What an EMS Quality-Improvement Review Could Examine
A pediatric arrest review should move beyond “protocol followed: yes/no.”
Consider:
- Was the arrest witnessed?
- Was bystander CPR provided?
- Was ventilation effective?
- Was epinephrine delivered at the intended time?
- Were reversible causes considered?
- Did rhythm interpretation remain accurate?
- Was CPR quality monitored?
- Were pauses minimized?
- Was transport initiated during CPR, and why?
- Were local TOR criteria met?
- Was medical control used as required?
- How was the family supported?
- Was death notification performed by someone trained for it?
- Did the crew receive post-event support?
Looking at these factors over several events can help an agency determine whether variation reflects justified clinical differences or inconsistent practice.
🎓 Instructor Note
For simulation, do not grade TOR as a single right-or-wrong moment. Grade the reasoning process. Learners should demonstrate that they recognized reversible causes, delivered high-quality resuscitation, knew local TOR criteria, understood transport implications, communicated with medical control when appropriate, and supported the family. This keeps the exercise focused on systems thinking rather than creating a simplistic pediatric “stop rule.”
🦺 LSE Training Connection
PALS and EMS education should prepare clinicians not only to run the algorithm, but also to understand the systems, communication, and decision-making surrounding pediatric resuscitation.
Request training for your organization or browse LSE courses.
Training You Can Count On. When Seconds Count.
Images are AI-generated educational illustrations, not photographs of the cited incidents or study participants. Displayed screens and documents are illustrative.
📚 Authoritative Sources
- Ramgopal S, et al. Futility and Termination of Resuscitation Variation for Pediatric Out-of-Hospital Cardiac Arrest. Pediatrics. 2026;158(3):e2026076981.
https://doi.org/10.1542/peds.2026-076981 - American Heart Association and American Academy of Pediatrics. 2025 Pediatric Advanced Life Support Guidelines.
https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/pediatric-advanced-life-support - American Heart Association. 2025 Systems of Care Guidelines.
https://cpr.heart.org/en/resuscitation-science/cpr-and-ecc-guidelines/systems-of-care/